Ebola response in Eastern Congo shows progress but remains massive 2026
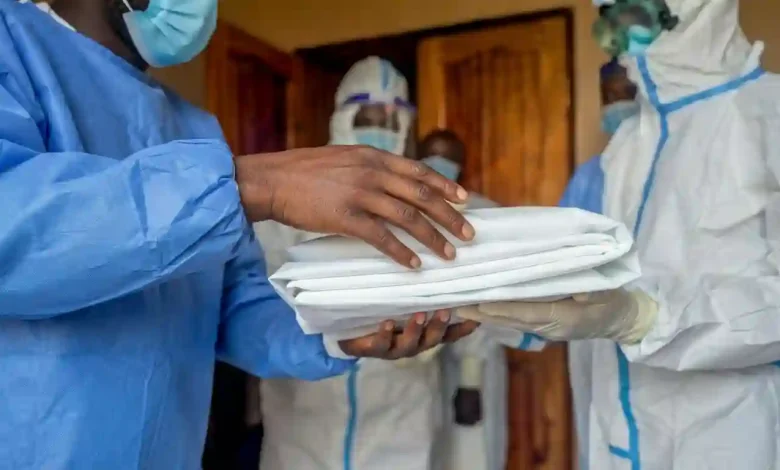
Table of Contents
Ebola response operations in eastern Democratic Republic of Congo (DRC) have reached a critical juncture, with United Nations officials reporting early, fragile signs of progress alongside sobering reminders that the deadly epidemic remains a massive global health emergency. Containment of the virus in this volatile region is one of the most complex humanitarian missions of the modern era. While localized clinical interventions are proving highly effective, systemic barriers including armed conflict, deep-rooted community distrust, and porous regional borders continue to hamper the speed of total eradication. Experts stress that while some transmission chains have been successfully broken, complete containment is still many months away.
The United Nations Assessment: Fragile Progress vs. Stubborn Growth
In a detailed assessment provided by high-ranking United Nations officials, the international community has been urged not to fall into complacency. The active deployment of localized healthcare teams and rapid-response units has begun to yield tangible results, particularly in previous hot spots where transmission rates have dropped. However, the virus has shown a persistent ability to flare up in newly cleared zones or migrate to hard-to-reach rural settlements. Effective mobilization requires a highly coordinated Ebola response to mitigate transmission and support localized healthcare systems before outbreaks metastasize further.
The dual nature of the current phase—where containment triumphs in one district are instantly offset by new cases in another—highlights the volatile epidemiology of Ebola in the DRC. Epidemiologists point out that the shifting geography of the virus is directly linked to population mobility. Traders, displaced families, and miners frequently travel through dense forest corridors, unknowingly carrying the pathogen across provincial lines. This high mobility complicates contact tracing, which is the cornerstone of any successful infectious disease containment strategy.
Julien Harneis on the Geneva Briefing
Speaking at a Geneva press briefing, Julien Harneis, the U.N. special Ebola coordinator, provided an honest and calculated overview of the situation on the ground. “It remains a deadly and a massive epidemic. There are some areas of progress, but nonetheless, in other areas, we continue to see growth in cases,” Harneis remarked. His statements underscore the complex nature of managing a public health crisis in an active conflict zone. Harneis highlighted that while mathematical modeling shows a downward trend in some urban centers, the rural hinterlands present an entirely different and more stubborn challenge.
Harneis emphasized that the international community must remain committed for the long haul. The operational overhead of maintaining treatment centers, secure transport routes, and community surveillance teams is astronomical. As international attention is frequently divided by other global crises, maintaining financial and logistical momentum is paramount. For instance, while international geopolitical crises like the Middle East war draw diplomatic focus, humanitarian agencies must ensure that resources for Sub-Saharan health emergencies do not dry up.
Geopolitical and Local Challenges in Eastern Congo
The eastern provinces of the Democratic Republic of Congo present a uniquely hostile environment for disease control. Decades of political instability have left the region with severely degraded public infrastructure. Roads are often impassable, electricity is non-existent in vast swathes of the territory, and clean water is a luxury. In such environments, basic infection control is a monumental task. Just as domestic health initiatives focus heavily on food safety in India to prevent localized enteric disease, the Congolese healthcare system must prioritize basic hygiene and water sanitation to prevent nosocomial Ebola transmission within local clinics.
Furthermore, the high density of informal mining camps creates perfect micro-environments for rapid transmission. These camps lack formal regulatory oversight, and workers live in close quarters with minimal access to healthcare. When an individual falls ill in these areas, they often seek traditional remedies or self-isolate in hidden locations, avoiding formal medical teams out of fear of isolation or stigmatization. By the time medical authorities are notified, multiple generations of transmission may have already occurred.
Security Instability and Community Distrust
Perhaps the most daunting obstacle to the Ebola response is the pervasive security instability. Dozens of active armed rebel groups operate in the eastern DRC, frequently launching attacks on civilians, government forces, and humanitarian workers. Treatment centers have been vandalized, and health workers have tragically lost their lives in the line of duty. This ongoing threat of violence forces medical teams to operate under heavy armed escorts, which can inadvertently alienate the local population, who may view the health response as an occupying military force rather than a humanitarian intervention.
Community resistance is also fueled by deep-seated political alienation. Many residents in the eastern provinces feel abandoned by the central government and are suspicious of international organizations. Rumors and misinformation about the origin of the virus and the purpose of the vaccines circulate widely on social media and through word-of-mouth. Unlike the highly localized cyclosporiasis outbreak that disrupted local communities in Western nations, Ebola presents a systemic threat that feeds on political distrust, making public education campaigns just as vital as physical medical supplies.
Comparative Analysis of Ebola Outbreaks
To understand the sheer scale of the current epidemic in eastern Congo, it is useful to analyze it alongside other historical and contemporary public health challenges. The table below outlines key parameters of Ebola outbreaks and containment variables:
| Outbreak / Region | Primary Transmission Drivers | Key Containment Tools | Major Operational Barriers |
|---|---|---|---|
| West Africa (2014-2016) | Urban density, regional travel | Contact tracing, safe burials | Weak health systems, slow global response |
| Eastern DRC (Current) | Armed conflict, mobile population | rVSV-ZEBOV vaccine, therapeutics | Active militia violence, deep community mistrust |
| Equateur Province (DRC) | River-based transport, remote forests | Targeted ring vaccination | Logistical isolation, vast travel distances |
As illustrated, the current outbreak in Eastern Congo is uniquely defined by active militia violence and community resistance, which prevents standard epidemiologic tools from being deployed safely. In some cases, critical supply chains face blockages similar to those seen when conflict disrupted Red Sea maritime security, impacting healthcare delivery to remote provincial outposts that rely entirely on consistent shipments of temperature-sensitive vaccines.
Healthcare Infrastructure and International Mobilization
Rebuilding and supporting local healthcare infrastructure is the only viable long-term solution to the Ebola threat. International NGOs and the World Health Organization (WHO) have worked to establish localized isolation wards, train local nurses and doctors, and distribute protective personal equipment (PPE). However, these efforts are often reactive rather than proactive. Long-term investment in regional health systems is required to detect pathogens before they escalate into full-scale epidemics.
Even as domestic jurisdictions tackle localized legal-medical actions—for instance, where Arizona has sued corporations over healthcare access or regulatory compliance—the international community must navigate complex sovereign laws in the DRC to establish stable healthcare corridors. Empowering local communities to take ownership of their health clinics is the most effective way to dismantle resistance and build lasting defense networks against infectious diseases.
Vaccination Drives and Therapeutic Innovations
The development and deployment of highly effective vaccines, such as the rVSV-ZEBOV, have revolutionized Ebola control. Ring vaccination—where contacts and contacts-of-contacts of confirmed cases are vaccinated—has successfully shielded thousands of vulnerable individuals. Additionally, the ongoing clinical trials of novel therapeutics offer fresh mechanisms for control, although deployment in active conflict zones remains a massive logistical challenge. Monoclonal antibody treatments have shown remarkable success in reducing mortality rates when administered early in the course of the disease.
However, the efficacy of these medical marvels relies entirely on cold-chain logistics. The vaccines must be stored at ultra-low temperatures, a nearly impossible task in equatorial forests without specialized solar-powered refrigeration units and highly trained logisticians. When supply chains break down, the potency of the vaccine is compromised, which parallels how public health regulatory bodies are increasingly scrutinized in consumer protection issues, such as the ongoing consumer litigation involving global brands. Regulatory compliance and clinical trial fidelity must be maintained even under extreme field conditions.
The Broader Context of Global Health Emergencies
The struggle to contain Ebola in the Democratic Republic of Congo is not an isolated event; it is a symptom of a broader crisis in global health security. As human populations expand into previously undisturbed ecosystems, the frequency of zoonotic spillover events is projected to increase. Ebola, which naturally resides in fruit bat populations, easily transitions to humans through the bushmeat trade or direct contact with contaminated forest environments. Preventing future outbreaks requires a holistic “One Health” approach that links environmental conservation, veterinary science, and human medicine.
International funding bodies must move away from emergency-response funding models toward sustained preventative investments. When resources are only deployed after an epidemic reaches crisis proportions, the cost in human lives and economic disruption is infinitely higher. Building robust epidemiological surveillance networks across Central Africa would allow local technicians to isolate index cases weeks before they can spread to major transit hubs, effectively neutralizing threats in their infancy.
The Road Ahead: How Long to Achieve Containment?
Achieving zero cases of Ebola in eastern Congo will require an unprecedented level of cooperation between local communities, regional administrative bodies, and international health agencies. U.N. officials have made it clear that we must prepare for a campaign that will last many more months, if not years. There are no quick fixes in a region defined by historical trauma and active armed conflict. The road ahead demands patience, adaptive strategies that respect local customs, and unwavering financial support from global donors.
Ultimately, the metrics of success will not just be measured in declining case numbers, but in the trust built between the doctors in protective gear and the families they serve. By integrating local leaders into the decision-making process, ensuring transparency in clinical trials, and providing comprehensive primary healthcare that goes beyond Ebola treatment, the global health community can finally hope to turn the tide against this devastating disease.
References / Authority Citations: