Hepatitis B Birth Dose Vaccine CDC Overhaul Sparks Debate 2026
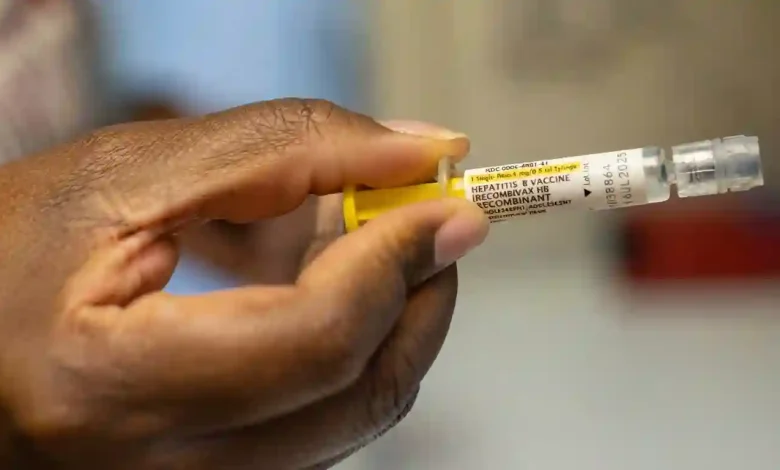
Table of Contents
Hepatitis B birth dose vaccine policy has reached an unprecedented regulatory and medical crossroad in the United States following sweeping revisions introduced under Health and Human Services leadership. For more than three decades, the Centers for Disease Control and Prevention maintained an unequivocal standard that every newborn infant receive an initial dose of the vaccine against hepatitis B virus within twenty-four hours of birth. That longstanding national consensus was dramatically dismantled when updated federal guidelines narrowed the recommendation, directing the neonatal dose solely to infants born to mothers with confirmed HBV infections or those whose infection status remains unknown at the time of delivery.
The administrative change forms a prominent component of the broader regulatory agenda championed by Health Secretary Robert F. Kennedy Jr., whose agency initiatives have prompted widespread debate across scientific and administrative institutions. Critics warn that abandoning universal prophylaxis creates perilous gaps in infant protection, particularly in diverse community settings where familial or non-maternal transmission dynamics remain prevalent. The policy shift occurs against a backdrop of broader debates surrounding federal health priorities, which have also intersected with issues like the Windward Bio advances in clinical drug development and parallel public debates regarding national medical mandates.
Hepatitis B Birth Dose Policy: The CDC Overhaul Explained
The revised federal doctrine rests upon the premise of tailored medical intervention rather than indiscriminate prophylaxis. Under the newly promulgated framework, obstetric and neonatal teams are instructed to establish maternal hepatitis B surface antigen status prior to administering the birth immunization. When a mother tests negative for HBsAg, the initial injection is deferred until subsequent routine well-child evaluations during early infancy, typically beginning at two months of age.
Proponents within federal administrative circles argue that this targeted protocol reduces aggregate pharmaceutical exposure for neonates born into low-risk domestic circumstances. They contend that modern prenatal screening mechanisms are sufficiently robust to capture maternal carriage of the virus, thereby safeguarding vulnerable infants without requiring universal intervention. However, prominent epidemiologists and infectious disease specialists caution that this operational pivot dangerously presumes flawless clinical execution, perfect prenatal care access, and negligible environmental exposure beyond the birthing parent. The controversy mirrors wider shifts in national immunization strategies, echoing ongoing public health debates such as the contentious childhood vaccine schedule changes executed across federal jurisdictions.
Kaiser Permanente Study: Evaluating Household Exposure Risks
Direct scientific pushback against the selective administration model arrived swiftly in a major clinical investigation led by Kaiser Permanente Northern California. Spearheaded by lead researcher Dr. Karen Jacobson, the exhaustive observational study examined medical records spanning 158,000 pediatric patients to assess the true prevalence of non-maternal HBV exposure in domestic environments.
The empirical findings revealed a stark vulnerability in the targeted vaccination philosophy. Researchers identified more than 2,000 children living in households where at least one resident family member—other than the biological mother—was actively infected with hepatitis B virus. These individuals included fathers, grandparents, aunts, uncles, and older siblings living within the shared residential perimeter.
“A child can be exposed to hepatitis B from anyone with an active infection, not just their mother,” Dr. Jacobson noted in a formal statement detailing the implications of the dataset. Because the revised CDC guidelines predicate birth immunization solely upon maternal serostatus, every child born to an uninfected mother within those 2,000 affected households would be discharged from the birthing hospital completely unvaccinated and biologically unprotected against domestic viral exposure during their most critical formative months. This structural vulnerability mirrors broader systematic strains observed across global healthcare networks, not unlike the institutional hurdles documented when an unforeseen measles outbreak catches unimmunized populations off guard.
Mechanisms of Early Childhood Hepatitis B Transmission
Hepatitis B virus is an extraordinarily resilient pathogen capable of surviving on environmental surfaces for seven days or longer while retaining complete infectious potency. While perinatal vertical transmission during labor and delivery is recognized as the most efficient vector, horizontal transmission during infancy remains an established clinical reality documented across global epidemiological literature.
In home settings, horizontal transmission occurs via inadvertent percutaneous or mucosal contact with minuscule amounts of blood, saliva, or exudative bodily fluids. Common daily interactions—such as sharing washcloths, nail clippers, toothbrushes, infant teething rings, or even minor skin abrasions suffered during common domestic accidents—can facilitate transmission if an infected household resident interacts closely with the neonate. In many respects, assessing household infection vectors requires the same multi-layered vigilance seen when clinical trials evaluate chronic viral suppressors, such as when bepirovirsen wins land designation in specialized antiviral clinical trials.
Crucially, an infant’s immune system lacks the immunological maturity required to clear an initial HBV exposure. When an adult contracts hepatitis B, more than ninety percent mount an acute immune response that clears the virus permanently. In sharp contrast, up to ninety percent of infants infected during their first year of life develop chronic, lifelong infection. This persistent carriage carries devastating long-term risks, including premature liver failure, cirrhosis, and hepatocellular carcinoma in early adulthood.
Historical Impact of Universal Neonatal Immunization
To grasp why the scientific community has responded with profound alarm, one must examine why universal birth dosing was established initially. Prior to 1991, the United States utilized a targeted vaccination strategy identical in philosophical structure to the newly implemented CDC policy. Under that former framework, vaccines were allocated only to infants born to mothers categorized as high-risk.
That historical targeted strategy failed utterly. Tens of thousands of infants slipped through institutional cracks due to transcription errors, lack of prenatal insurance, unrecorded laboratory results, or non-maternal household exposures. Acknowledging this systemic breakdown, public health authorities adopted universal birth vaccination in 1991. The results were immediate and historic: pediatric hepatitis B cases declined by more than ninety-five percent across the United States over the subsequent two decades, virtually eliminating acute infant hepatitis B in domestic hospital environments. Public health infrastructure had effectively transformed the birth dose into an infallible safety net, creating a protective barrier comparable to how broader preventative regimens safeguard populations when flu vaccination urged initiatives are rolled out ahead of seasonal outbreaks.
Comparative Analysis: Universal vs Risk-Targeted Protocols
The operational divergences between the two paradigms have significant clinical, legal, and epidemiological implications for healthcare delivery organizations across the nation.
| Evaluation Metric | Universal Birth Dose Protocol (Pre-Reorganization) | Targeted Maternal-Only Protocol (Revised Policy) |
|---|---|---|
| Primary Clinical Target | All newborn infants regardless of parental serostatus | Only infants of HBsAg-positive or unknown-status mothers |
| Timing of Initial Dose | Within 24 hours of delivery prior to hospital discharge | Deferred to 2 months of age if maternal test is negative |
| Protection Against Household Transmission | Immediate, robust protection against all cohabitants | Zero biological protection against infected cohabitants for 60+ days |
| Systemic Resilience to Administrative Error | Extremely high; universal protocol avoids screening reliance | Fragile; vulnerable to missed labs, paperwork errors, or false negatives |
| Pediatric Advisory Support | Endorsed by AAP, AAFP, and viral hepatitis specialists | Heavily contested by major professional pediatric societies |
Pediatric Societies and Public Health Infrastructure Reactions
Major medical organizations have reacted with intense apprehension to the revised directives. The American Academy of Pediatrics, alongside the American Academy of Family Physicians, reaffirmed their independent professional clinical guidance advising clinicians to continue administering universal birth doses regardless of federal policy modifications. Pediatricians emphasize that the hospital delivery setting represents the single most dependable clinical opportunity to guarantee immunization before socioeconomic or logistical hurdles impede outpatient access.
Clinicians also express concern over how shifting federal guidelines confuse parents and undermine foundational confidence in preventative medicine. As public messaging fractures along ideological and regulatory fault lines, clinicians face significant difficulties explaining the necessity of disease prevention to hesitant parents. This environment of public skepticism has broad precedents, resembling the consumer anxiety and regulatory scrutiny documented in legal battles surrounding Tylenol autism lawsuits and other contentious healthcare disputes.
The Fallibility of Maternal-Only Screening Frameworks
The foundational assumption of the new CDC guideline is that maternal screening will accurately flag every child who genuinely requires immediate intervention. Yet clinical reality frequently diverges from theoretical policy design. In practical obstetrics, prenatal care access is distributed unequally across economic and geographic demographics. Many pregnant women arrive at delivery units with fragmented prenatal records, while laboratory processing delays during rapid labor can leave a mother’s viral status unresolved at the moment of birth.
Moreover, prenatal blood tests are not completely immune to technical errors, collection contamination, or false-negative readouts. Under the universal framework, an administrative or laboratory error had minimal consequence because the infant received prophylactic protection regardless of maternal lab files. Under the revised targeted paradigm, an unflagged laboratory error directly results in a completely unprotected newborn. The systemic risks inherent in restructuring clinical thresholds mirror broader pharmaceutical and administrative complexities, similar to discussions around managing long-term therapeutic regimens like GLP-1 effects patient profiles where altering clinical protocols triggers unanticipated physiological consequences.
Epidemiological Projections and Future Public Health Challenges
Looking ahead, epidemiological modeling suggests that scaling back universal neonatal protection will inevitably reignite pediatric HBV incidence in vulnerable metropolitan and rural areas alike. Because chronic hepatitis B remains clinically silent for years—or even decades—the full toll of newly acquired childhood infections may not fully manifest in national registries until years down the road, when affected individuals present with advanced hepatic cirrhosis or liver malignancies in adulthood.
The financial burdens on the broader healthcare system are equally profound. The expense of managing end-stage liver disease, hepatic transplantation, and chronic antiviral management far outstrips the negligible budgetary cost of an infant vaccine series. As state health departments, hospital systems, and medical boards navigate these conflicting directives, the tension between federal health ideology and empirical clinical science will remain one of the most consequential public health battlegrounds of the modern era, compelling institutions to reassess preventative care strategies across the spectrum.




